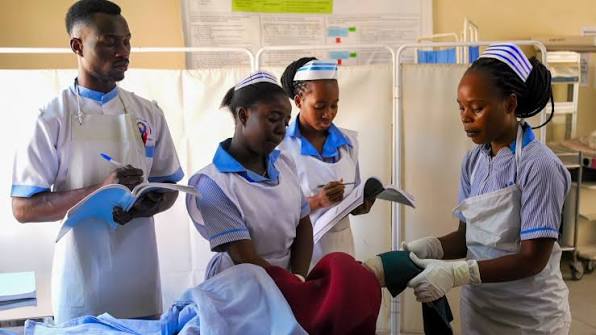
Zambia’s removal from the World Health Organization’s health workforce safeguards list would be a welcome development. But the real test is not whether the country has moved off an international list. It is whether patients can access qualified health workers when and where they need them.
Zambia’s health sector has reason to welcome progress in its international standing on health workforce issues. But any suggestion that exiting the World Health Organization’s (WHO) health workforce ‘red list’ means the country has solved its shortage of doctors, nurses and midwives would be premature.
The distinction matters because the WHO list is not a scoreboard of government performance. It is a policy instrument designed to identify countries facing serious health workforce vulnerabilities and discourage aggressive international recruitment that could worsen those shortages.
To understand what Zambia’s exit means, it is necessary to understand what the list measures, what may have changed and what remains unresolved.
What is the WHO red list?
Formally known as the WHO Health Workforce Support and Safeguards List, it identifies countries facing particularly pressing health workforce challenges in their efforts to achieve universal health coverage.
Under the previous framework, countries were assessed using two broad indicators: the density of doctors, nurses and midwives relative to their population, and their Universal Health Coverage service coverage index.
The 2023 list included 55 countries, of which 37 were in the WHO African Region. The objective was not to prevent health workers from seeking opportunities abroad, but to discourage active international recruitment from countries whose health systems could ill afford to lose additional personnel.
The safeguards were intended to encourage more responsible recruitment, including government-to-government arrangements that protect the interests of both countries and support the strengthening of health systems in countries supplying health workers. <escape></escape>
In other words, being on the list did not mean a country was prohibited from exporting health workers. Nor did leaving it necessarily mean the country had enough health workers to meet every patient's needs.
What changed?
The important development is that the WHO framework has evolved.
In May 2026, WHO announced amendments to its Global Code of Practice on the International Recruitment of Health Personnel. The changes included stronger provisions on care workers, recruitment during emergencies and co-investment in health systems so that international recruitment generates benefits for both source and destination countries. <escape></escape>
The updated safeguards framework also introduces greater flexibility. Countries identified through technical indicators can request an exemption from the standard safeguards, while countries not initially identified can request to be included. The revised list therefore incorporates countries' positions alongside the technical assessment. <escape></escape>
This is an important qualification when interpreting Zambia's reported exit. Removal from the list may reflect changes in the technical assessment, a country's position under the revised framework, or a combination of factors. It should not automatically be presented as proof that Zambia has eliminated its workforce deficit.
The specific explanation for Zambia's status should be established from the final WHO list and the accompanying country-level assessment. Without that evidence, it would be premature to attribute the change to new recruitment, improved retention or a dramatic expansion in the health workforce.
Zambia has made progress, but the baseline matters
There is evidence of progress in the country's ability to monitor its health workforce.
In August 2026, WHO recognised Zambia for its improvement in reporting health workforce data. Zambia ranked first in the WHO African Region and third globally in the 2024 National Health Workforce Accounts reporting cycle, with a data availability score of 94%, up from 81% in the previous cycle. <escape></escape>
This is a meaningful achievement. Better data allow policymakers to identify vacancies, understand workforce distribution and make more informed decisions about training, recruitment and deployment.
But better measurement and more health workers are two different things.
A country can improve its workforce information systems without immediately filling vacant positions. It can recruit thousands of health workers while still experiencing shortages if population growth, disease burdens, staff attrition and the expansion of services outpace recruitment.
Historical figures illustrate the scale of Zambia's challenge. WHO's 2025–2027 country cooperation strategy reported that the Ministry of Health's establishment increased from 63,057 positions in 2016 to 126,831 in 2021. Yet only 63,878 positions were occupied in 2021, leaving a vacancy rate of approximately 52%. <escape></escape>
Those figures are historical, not a measure of today's vacancy rate. They nevertheless demonstrate why the country needs current, comparable data on authorised positions, filled posts and actual staffing levels before declaring victory.
The real problem is not just producing health workers
Zambia's workforce challenge cannot be solved by training more doctors and nurses alone.
Training is only the first stage of a much longer process. Graduates must be absorbed into funded positions, deployed to facilities where they are needed, equipped to work effectively and given sufficient reasons to remain in the public health system.
The WHO's 2026 assessment of the African health workforce highlights a wider continental paradox: countries are producing more health workers even as shortages persist, trained professionals struggle to find jobs and migration pressures intensify. WHO estimated that 943,000 trained health workers across Africa were unemployed in 2024. <escape></escape>
The implication for Zambia is straightforward. Expanding training without creating employment opportunities can leave graduates unemployed while facilities remain understaffed. Recruiting workers without addressing working conditions can produce temporary gains that are gradually eroded by resignations and migration.
And recruiting workers for urban hospitals does not necessarily resolve shortages in rural health centres.
The relevant policy question is therefore not simply how many health workers Zambia has trained or recruited. It is how many are working, where they are deployed, what services they provide and whether the health system can retain them.
Does this mean the shortage is over?
No. The list and the shortage measure different things.
WHO's 2026 guidance makes clear that its global benchmark of 49 doctors, nurses and midwives per 10,000 people is a statistical threshold used in identifying workforce vulnerability, not a universal recommendation for every country. The appropriate workforce depends on population needs, disease patterns, skills and how services are organised. <escape></escape>
Even if Zambia no longer falls under the list's safeguards, shortages may persist in particular professions, districts and facilities. The national picture can improve while some communities continue to struggle to access basic healthcare.
The more meaningful test is whether patients are waiting less time, health facilities have the staff required to operate effectively, rural communities can access skilled personnel and essential services are consistently available.
These outcomes require more than a change in international classification. They require sustained investment and better workforce management.
What should Zambia do next?
First, the government should publish an updated health workforce picture. The public needs to know the number of established positions, filled posts and vacancies, disaggregated by profession, province and facility type. Recruitment announcements are useful, but they should be accompanied by evidence showing how much of the staffing gap has actually closed.
Second, recruitment must be matched to the resources required to employ and retain health workers. Training institutions can produce graduates, but the government must provide funded positions, competitive and reliable remuneration, equipment and workable conditions. Otherwise, the country risks financing training without fully benefiting from the skills it produces.
Third, workforce deployment must become more responsive to need. The availability of doctors, nurses and midwives in Lusaka is not a substitute for their availability in remote districts. Incentives for rural service, career development, appropriate housing and professional support can help address persistent geographical imbalances.
Finally, Zambia should use its improving workforce data to strengthen accountability. Annual reporting should track recruitment against vacancies, attrition, migration, staff distribution and the availability of personnel at frontline facilities. The aim should be to measure whether the system is becoming more capable of delivering healthcare, rather than simply whether administrative targets have been met.
The bigger picture
Zambia's reported exit from the WHO health workforce safeguards list should be welcomed, but understood in the right context.
It may represent a positive development in the country's international classification. Zambia's progress in workforce data reporting is also encouraging. Both deserve recognition.
However, neither achievement, on its own, establishes that the country has sufficient health workers or that staffing shortages have been resolved.
There is a broader lesson here about how governments measure progress. International recognition and improved indicators matter, but they are not the final objective. The purpose of workforce policy is to ensure that a patient arriving at a health facility can receive timely care from a qualified professional.
That is the standard against which Zambia's progress should ultimately be judged.
Leaving the red list may be a milestone. Ending the shortage requires a different kind of progress: enough health workers, in the right places, with the resources and conditions to do their jobs.